Thursday, September 17, 2026

Why Did My Hernia Come Back?

What the research actually says about hernia recurrence, and what can be done about it

You had the surgery. You did the recovery. And then, months or years later, you felt the bulge again.

If you are reading this, you may be angry, exhausted, or quietly convinced you did something wrong. Many patients who come to The Iskandar Complex Hernia Center have been living with pain for years, and some feel embarrassed to walk back into a surgeon’s office at all.

Here is the first thing worth knowing: you are not an unusual case. Roughly one in five incisional hernia repairs is performed on a hernia that has already come back at least once (Hernia, Springer Nature, 2020). Recurrence is one of the central, unsolved problems in abdominal wall surgery, and it is studied intensely precisely because it is so common.

The second thing worth knowing is that recurrence usually has specific, identifiable reasons. Most of them have far more to do with how the hernia was repaired, and how the wound healed, than with anything you did.

This article walks through what the published evidence says. It is deliberately heavy on numbers, because you deserve the real ones.
lasting hernia repair

How often do hernias actually recur?

Contemporary estimates of recurrence after ventral hernia repair range from 30% to 80%, depending on the population studied and how long patients are followed (JAMA Surgery, 2024).

That range is uncomfortably wide. The most useful modern American data comes from the Abdominal Core Health Quality Collaborative (ACHQC), a national surgical quality registry. In a 2024 study published in JAMA Surgery, researchers tracked 35,433 U.S. patients who had already undergone at least one ventral hernia repair. What they found is that recurrence is not a single event with a single probability, it is a risk that accumulates, year after year.

Cumulative recurrence after ventral hernia repair (patients with a prior mesh repair)

Time since repair Cumulative recurrence
6 months 2.8%
1 year 8.0%
2 years 19.7%
3 years 29.3%
4 years 38.5%
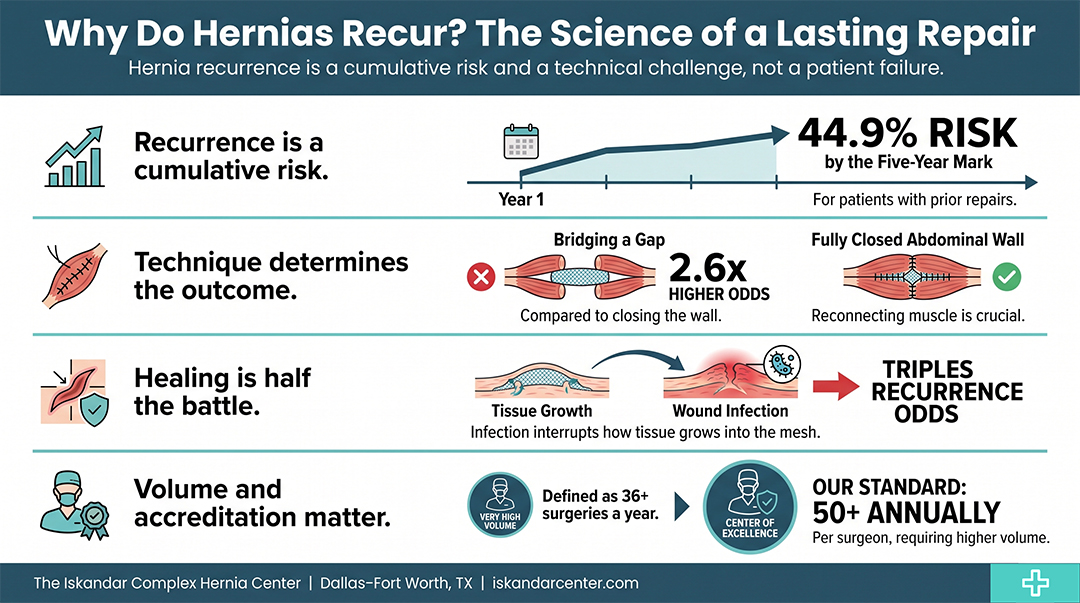
5 years 44.9%

Source: Year-Over-Year Ventral Hernia Recurrence Rates and Risk Factors, JAMA Surgery, 2024 (ACHQC registry, 35,433 patients, 2012–2022)

The curve keeps climbing. A separate nationwide analysis of 45,773 hernia repairs in Denmark found that operations for recurrence were still accumulating fifteen years after the original surgery, reaching 18–20% for incisional hernias (BJS Open, 2024). And because that figure counts only patients who went back for another operation, it almost certainly understates the true number. Plenty of people live with a recurrence without ever having it repaired again.

What this means for you: the fact that your hernia returned does not make you an outlier or a failure. It makes you part of a very large, very well-documented group.

When do recurrences show up?

This is the question patients ask most often at follow-up appointments: “It’s been three years. Am I in the clear?”

The honest answer is mostly, but not entirely. Data from the Herniamed registry, one of the largest hernia registries in the world, shows a clear pattern for incisional hernias:

When the recurrence appeared Share of all recurrences Running total
Within the first year 35.2% 35.2%
Second year 20.5% 55.7%
Third year 10.0% 65.7%
Fourth year 6.1% 71.8%
Fifth year 7.0% 78.8%
Years 5–10 ~2.6% per year ~92% by year 10

Source: How Long Do We Need to Follow-Up Our Hernia Patients to Find the Real Recurrence Rate? Frontiers in Surgery, 2015

More than a third of recurrences declare themselves in the first twelve months. Two-thirds have appeared by year three. But recurrences continue to surface for a decade or more, which is exactly why long-term follow-up after complex hernia repair is not an upsell. It is the natural history of the disease.

Reason 1: How the repair was performed

This is the part most patients are never told, and it is where the largest effects live.

The single best synthesis of this question is a 2021 systematic review and meta-analysis in BJS Open, which screened 18,214 studies and pooled data from 274 of them to identify what actually predicts recurrence (BJS Open, 2021). Nearly every number in the sections that follow comes from that analysis.

Stitches alone don’t hold. In a landmark randomized trial, incisional hernias repaired with sutures alone recurred in 63% of patients at ten years, compared with 32% when mesh was used. Even for small hernias, the split was 67% versus 17%. The authors’ conclusion was blunt: suture repair of incisional hernia should be abandoned (Annals of Surgery, 2004).

That trial ran in the 1990s, and it is the reason the field changed. It does not describe your odds today, it describes why surgeons stopped repairing these hernias with stitches. Across 48 modern studies, mesh reinforcement reduces the odds of recurrence by roughly a third compared with suture-only repair.

Whether the muscles were actually brought back together. When a hernia defect is too wide to close, some surgeons “bridge” it, laying mesh across the gap like a tarp over a hole, without reconnecting the abdominal wall muscles. It is faster. It is also associated with a 2.6-fold increase in the odds of recurrence compared with repairs where the abdominal wall is fully closed.

This is arguably the most important technical concept in this entire article, and we return to it below, because there is now a well-established way to solve it.

Where the mesh was placed. Not all mesh repairs are the same operation. Mesh positioned in the retromuscular plane, behind the muscle, recurs significantly less often than mesh laid on top of the abdominal wall (onlay) or placed inside the abdominal cavity.

What the mesh was made of. This one surprises patients: biologic mesh recurred roughly twice as often as synthetic mesh in ventral hernia repair. A randomized trial confirmed it even in contaminated surgical fields, where biologic mesh has traditionally been favored; two-year recurrence was 20.5% with biologic mesh versus 5.6% with synthetic (JAMA Surgery, 2022). Extended follow-up out to a median of 5.4 years found the same pattern held: 23.6% versus 11.8% (American College of Surgeons, 2026).

None of this means your prior surgeon did anything wrong. Complex hernia repair is genuinely difficult surgery; techniques have changed substantially in the last decade, and an approach that was reasonable in 2015 may not be the approach a specialist would choose in 2026.

Reason 2: How the wound healed

Here is the finding that reframes everything, and the one almost nobody explains to patients:

A wound infection after hernia repair more than triples the odds that the hernia will recur.

Not by 20%. Not by half. More than three times, an odds ratio of 3.21 across 24 studies. And it is not just infection. Every category of wound complication independently predicts recurrence:

Postoperative complication Increase in odds of recurrence
Any surgical-site occurrence 3.65×
Any postoperative complication 3.34×
Hematoma (blood collection) 3.33×
Wound infection 3.21×
Wound separation (dehiscence) 2.21×
Seroma (fluid collection) 1.99×

Source: Identifying predictors of ventral hernia recurrence, BJS Open, 2021

These are the largest effect sizes in the entire recurrence literature, larger than obesity, larger than smoking, larger than diabetes. The landmark 2004 randomized trial found the same thing independently: wound infection was a significant predictor of recurrence.

Why? A repair has to heal to hold. Mesh does not work by mechanical strength alone; it works because your own tissue grows into it. Infection, fluid, and inflammation interrupt that process at exactly the moment it matters most.

Recurrence, in other words, is often a healing problem as much as a mechanical one. That has a direct consequence for how these operations should be planned, and by whom.

Reason 3: Factors in your own body

These matter. They are also, in most cases, the smallest of the three categories, which is worth not self-criticizing if you have been blaming yourself.

Risk factor Increase in odds of recurrence
Long-term steroid use 2.08×
A hernia that has already recurred once 1.88×
An incisional hernia (vs. a hernia with no prior surgery) 1.79×
BMI over 30 1.54×
COPD 1.53×
ASA class III–IV (significant medical complexity) 1.46×
Diabetes 1.36×
Smoking 1.34×

Source: Identifying predictors of ventral hernia recurrence, BJS Open, 2021

Compare those numbers to the table above. Smoking raises your odds by about a third. A wound infection more than triples them. Both matter, but the surgical and healing factors dominate.

There are mechanisms behind the modifiable risks, and they are worth understanding rather than moralizing about. Smoking reduces oxygen delivery to healing tissue and blunts the inflammatory response that knits a repair together. Excess abdominal weight raises intra-abdominal pressure, working steadily against the repair from the inside. Poorly controlled blood sugar impairs wound healing. These are not character failures. They are biology, and biology can be worked on.

The line in bold deserves special attention. A hernia that has already recurred once is significantly more likely to recur again. Every previous operation leaves scar tissue, disrupts blood supply, and distorts the anatomy. This is the single most important reason a recurrent hernia should not be treated as a repeat of the same operation, and why it belongs with a surgeon who does this work constantly.

Why every website gives you a different number on Recurring Hernias

You have probably noticed that recurrence rates online range from “rare” to “more likely than not.” There is a reason.

In that review of 274 studies, only 66 of them (24%) even defined what counted as a recurrence, and among those that did, researchers used 41 different definitions and 67 different detection methods. The median follow-up was just 24 months, which, given the timeline above, means most studies stop counting before a third of recurrences have appeared.

Anyone quoting you a single confident recurrence percentage is oversimplifying. What the evidence supports is not one number, but a set of factors, most of which are actionable.

So what actually works? Two answers, and you need both.

The procedures have genuinely improved

The bridged-repair problem described earlier, mesh spanning a gap the surgeon could not close, is the exact problem that modern posterior component separation was designed to solve. The transversus abdominis release (TAR) technique allows the surgeon to release the abdominal wall from behind, move the muscles back to the midline, close the fascia properly, and place a large mesh in the retromuscular plane where the evidence says it performs best.

The difference in the published results is substantial:

Older anterior component separation Modern posterior component separation (TAR)
Wound complications 20–35% ~15%
Recurrence at 2 years ~13% ~4%

Source: Systematic review of transversus abdominis release in complex abdominal wall reconstruction, Hernia, Springer Nature, 2019

That is real progress, and it is why a hernia that was called “unfixable” several years ago may be very fixable today.

But the surgeon performing them matters enormously

Advanced techniques only produce advanced results in hands that use them often. The evidence on this is unusually direct.

A 2024 study in JAMA Network Open examined 23,580 surgeons performing robotic-assisted ventral hernia repair and found that roughly 19 cases were required before a surgeon’s long-term reoperation rates matched those of established open and laparoscopic approaches. Fewer than 6% of surgeons ever exceeded that volume (JAMA Network Open, 2024).

Read that again. The technique works, but most surgeons performing it have not done it enough times for it to work as well as it should.

The published volume thresholds in hernia surgery are sobering in their modesty. In the peer-reviewed literature, a surgeon performing fewer than 12 hernia repairs a year is classified as low volume. More than 36 a year qualifies as very high volume (Hernia group analysis, 2022).

This is where accreditation stops being a plaque on a wall and starts being a number.

What accreditation actually requires

Dr. Mazen E. Iskandar, MD, FACS is a Surgeon of Excellence in Hernia Surgery, accredited by the Surgical Review Corporation (SRC) in January 2024. In October 2025, The Iskandar Complex Hernia Center was accredited as a Hernia Center of Excellence, one of only two in North Texas.

SRC is an independent, nonprofit patient safety organization. Its accreditation is merit-based, and its published requirements for the Center of Excellence in Hernia Surgery program include (Surgical Review Corporation):

  • Each accredited surgeon must perform at least 50 qualifying hernia surgeries per year, and at least 125 over their career
  • The facility must perform at least 100 qualifying hernia surgeries annually
  • Prospective outcomes data on every hernia patient must be collected in a qualifying outcomes database
  • A full complement of consultative services, including a wound care specialist, infectious disease specialist, and nutritionist
  • Standardized clinical pathways and operative documentation
  • Verification through on-site inspection and chart audit

Set that first number against the research. The peer-reviewed literature defines very high volume as more than 36 hernia repairs a year. SRC’s minimum annual requirement is 50, the accreditation floor sits above the threshold the medical literature calls very high volume.

And look at the rest of that list against what this article has established. The evidence says wound complications are the strongest predictor of recurrence, and the accreditation requires a wound care specialist, an infectious disease specialist, and a nutritionist. The evidence says most recurrence data is poorly tracked, and the accreditation requires prospective outcomes collection on every patient.

The accreditation asks for precisely the infrastructure that the research says determines whether a repair lasts.

What this means for you

If your hernia has recurred, the evidence says several things at once.

It says this is common, and not your fault. It says the strongest predictors of recurrence are how the repair was constructed and how the wound healed, not your willpower. It says the things you can change, like smoking and blood sugar and weight, are worth changing, and that many patients never get the chance to address them: as many as 25% of people arrive at hernia surgery with a high-risk characteristic that was never optimized (JAMA Network Open, 2021).

And it says that a recurrent hernia is a harder operation than the first one, which is exactly why it should not be approached as a repeat of the first one.

Being told “nothing more can be done” is not the same as nothing more being possible. Many patients arrive at The Iskandar Complex Hernia Center after being turned away elsewhere, unaware that the options had changed. Dr. Iskandar offers the full range of techniques, robotic-assisted, laparoscopic, and open, including component separation and abdominal wall reconstruction, and will not promise something he cannot accomplish.

If your hernia has come back, don’t waste time wondering if there’s help for you.

Schedule a consultation with The Iskandar Complex Hernia Center.

Medically reviewed by Dr. Mazen E. Iskandar, MD, FACS, Surgeon of Excellence in Hernia SurgeryT

Sources

  1. Bhardwaj P, Huayllani MT, Olson MA, Janis JE. Year-Over-Year Ventral Hernia Recurrence Rates and Risk Factors. JAMA Surgery. 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC10974689/
  2. Parker SG, Mallett S, Quinn L, et al. Identifying predictors of ventral hernia recurrence: systematic review and meta-analysis. BJS Open. 2021. https://academic.oup.com/bjsopen/article/5/2/zraa071/6220253
  3. Burger JWA, Luijendijk RW, Hop WCJ, et al. Long-term follow-up of a randomized controlled trial of suture versus mesh repair of incisional hernia. Annals of Surgery. 2004. https://pmc.ncbi.nlm.nih.gov/articles/PMC1356459/
  4. Köckerling F, et al. How Long Do We Need to Follow-Up Our Hernia Patients to Find the Real Recurrence Rate? Frontiers in Surgery. 2015. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4468742/
  5. Prospective nationwide analysis of long-term recurrence rates after elective ventral, incisional and parastomal hernia repairs. BJS Open. 2024. https://academic.oup.com/bjsopen/article/8/4/zrae070/7705370
  6. Wegdam JA, et al. Systematic review of transversus abdominis release in complex abdominal wall reconstruction. Hernia. 2019. https://link.springer.com/article/10.1007/s10029-018-1870-5
  7. Learning Curves for Robotic-Assisted Ventral Hernia Repair. JAMA Network Open. 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC11615711/
  8. Biologic vs Synthetic Mesh for Single-stage Repair of Contaminated Ventral Hernias: A Randomized Clinical Trial. JAMA Surgery. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC8771431/
  9. Howard R, Delaney L, Telem D, et al. Development and Implementation of Preoperative Optimization for High-Risk Patients With Abdominal Wall Hernia. JAMA Network Open. 2021. https://pubmed.ncbi.nlm.nih.gov/33978723/
  10. Recurrent incisional hernia repair: surgical outcomes in correlation with body-mass index. Hernia. 2020. https://link.springer.com/article/10.1007/s10029-020-02320-5
  11. Center of Excellence in Hernia Surgery, Program Requirements. Surgical Review Corporation.https://www.surgicalreview.org/wp-content/uploads/2021/05/COE-Hernia-Surgery-051321.pdf
  12. Transversus abdominis release (TAR) procedure: a retrospective analysis of an abdominal wall reconstruction group. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC9622848/


source https://iskandarcenter.com/hernia-surgery/why-did-my-hernia-come-back/

Monday, September 14, 2026

What DFW Hernia Surgeon Accepts Insurance?

Patients weighing hernia surgery in Dallas–Fort Worth usually arrive with the same worry: not whether the operation is covered, but whether the surgeon they want is. The answer sits in the difference between coverage and participation.

What DFW hernia surgeon accepts insurance?

Hernia repair is a medically covered surgical service, so the real variable for a Dallas–Fort Worth patient is not the procedure but the provider. A surgeon and a facility participate separately. One can be in-network while the other is not, which is why benefits verification before scheduling confirms both, along with any prior authorization the plan requires.

The Iskandar Complex Hernia Center, led by Dr. Mazen E. Iskandar, MD, FACS, operates within Baylor Scott & White Medical Center – Waxahachie and verifies benefits before scheduling. The Iskandar Center participates with many major health insurance plans. Plan participation changes, so current status is confirmed directly with the Iskandar Center.

Hernia Surgeon Insurance

Does insurance cover hernia surgery?

Hernia surgery is generally covered when a physician documents that the repair is medically necessary, because a hernia is a structural defect rather than a cosmetic concern. ACA-compliant plans cover hospitalization and outpatient surgical services as essential health benefits. The live questions are prior authorization, network participation, and the patient’s share of the cost. Not the category itself.

What makes a hernia repair count as medically necessary rather than elective?

Payers generally treat a hernia repair as medically necessary when the hernia is symptomatic, causing pain or limiting normal function, or when it carries risk of incarceration or strangulation. Elective means scheduled, not optional. Medical-necessity definitions vary materially between payers, and an asymptomatic hernia is the case most likely to be questioned during prior authorization.

Are robotic-assisted hernia repairs covered on the same terms as open repairs in DFW?

Coverage terms for hernia repair are set by medical necessity, not by surgical approach, and robotic assistance carries no separate procedure code. The American Medical Association set that convention in 2007, so a robotic repair is reported under the code for the equivalent laparoscopic procedure. Facility charges can still differ, because equipment cost sits in the facility fee. As of 2026, network participation for a given approach remains plan-specific across Dallas–Fort Worth.

Dr. Iskandar performs robotic-assisted, laparoscopic, and open hernia repairs, including component separation and abdominal wall reconstruction. The approach is selected case by case rather than by default. The Iskandar Complex Hernia Center holds the Surgical Review Corporation’s Hernia Center of Excellence designation, one of only two in North Texas.

What documentation does an insurer typically require before approving hernia surgery?

Insurers typically require clinical notes describing the hernia and its symptoms, imaging where obtained, documentation of functional limitation, and a record of any conservative management already attempted. Most commercial plans require prior authorization before an elective repair. The surgeon’s office assembles and submits that package, and the plan reviews it against its own medical-necessity policy.

Does insurance treat a recurrent or revision hernia repair differently from a first repair?

A recurrent hernia repair is generally covered on the same medical-necessity basis as a first repair, and a prior repair that failed does not by itself disqualify a claim. Recurrence is a known outcome of hernia surgery. Revision repairs are reported under distinct procedure codes, and payers may review the documentation more closely, so the operative report from the earlier repair becomes part of the authorization package.

What out-of-pocket costs typically remain after insurance for hernia surgery in DFW?

Remaining out-of-pocket exposure after insurance is set by the plan’s deductible, coinsurance, and out-of-pocket maximum. A hernia surgery episode in Dallas–Fort Worth generates separate charges from the surgeon, the facility, and anesthesia, and each carries its own network status. Timing matters too. Where the plan year stands determines how much of the deductible has already been met.

Experience renowned expertise and unparalleled compassion from the leader in hernia repair.

What changes about coverage when a hernia repair is done by an out-of-network specialist?

Federal surprise-billing protections do not extend to a patient who knowingly selects an out-of-network surgeon for a scheduled hernia repair. Those protections cover emergencies, out-of-network care delivered at an in-network facility, and providers a patient cannot choose, such as anesthesiology. For a planned procedure with a chosen specialist, the out-of-network surgeon may present a federal notice-and-consent form that waives balance-billing protection. The patient may decline and seek in-network care. Whether a given surgeon is in-network is confirmed against the plans that surgeon participates in.

How does a patient appeal a denied hernia surgery claim in Texas?

A denied hernia surgery claim is appealed internally with the plan first, and the denial letter states the reason and the deadline. What happens next depends on plan type, which the denial letter and the insurance card identify. As of 2026, fully insured Texas plans route to an independent review organization, requested on Texas Department of Insurance form LHL009 and submitted to the carrier or utilization review agent that issued the denial. Self-funded employer plans follow a federal process instead.

The Iskandar Complex Hernia Center prepares and submits the clinical documentation supporting prior authorization, and assists when a denial calls for additional records. Dr. Iskandar, a board-certified general surgeon and Surgeon of Excellence in Hernia Surgery, serves Dallas–Fort Worth patients from Waxahachie. Patients do not navigate that process alone.

Key Takeaways: Hernia Surgery Insurance Coverage in Dallas–Fort Worth

  • Hernia repair is generally covered when documented as medically necessary: symptomatic, limiting normal function, or carrying risk of incarceration or strangulation.
  • A surgical episode generates separate charges from the surgeon, the facility, and anesthesia, each carrying its own network status.
  • Robotic-assisted hernia repair is reported under the same procedure code as the equivalent laparoscopic repair, though facility charges may differ.
  • Federal surprise-billing protections do not apply when a patient knowingly selects an out-of-network surgeon for a scheduled procedure.
  • A denied claim is appealed internally first; the external review that follows is routed by plan type, not by geography.

Benefits and network participation are verified for both the surgeon and the facility before anything is scheduled. Schedule a consultation at The Iskandar Complex Hernia Center, and the authorization paperwork is handled from there.

Related Resources

Medically Reviewed By:
Mazen Iskandar, MD, FACS
Board-Certified General Surgeon
Fellowship-Trained Minimally Invasive & Bariatric Surgeon
SRC-Accredited Surgeon of Excellence in Hernia Surgery
Last reviewed September 14, 2026


source https://iskandarcenter.com/hernia-surgeon/what-dfw-hernia-surgeon-accepts-insurance/

Wednesday, September 9, 2026

Is Hernia Surgery Safe for Elderly Patients?

Families weighing hernia repair for an older parent are usually working with the same two facts: a surgeon has raised the option, and someone in the family has raised his age. This article addresses what surgeons actually assess when the patient is 75, 85, or older.

Is hernia surgery safe for elderly patients?

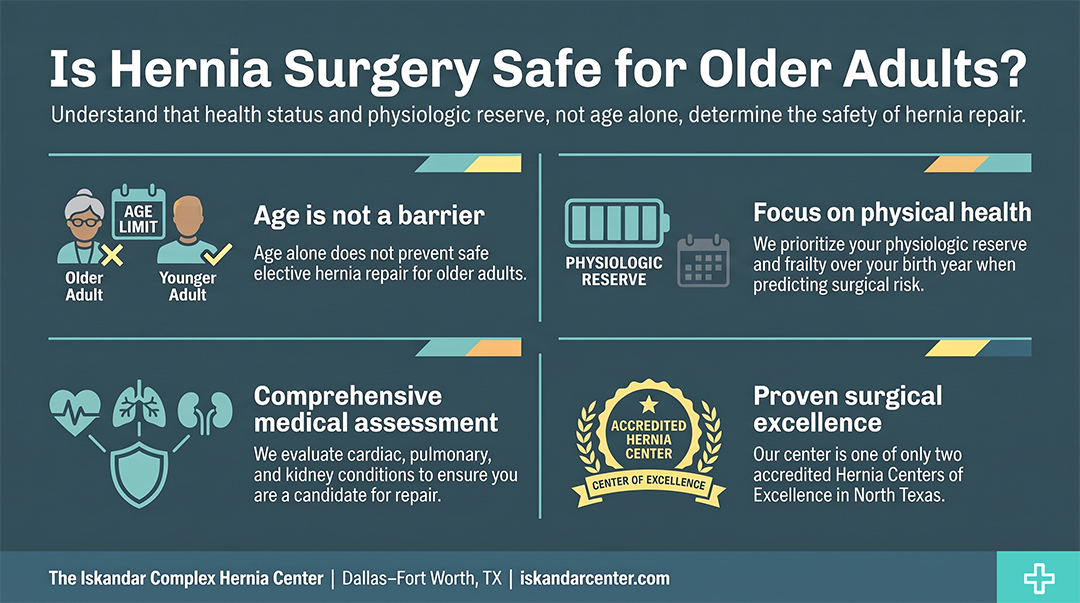
Elective hernia repair is performed safely in older adults, and age alone is not a contraindication. What predicts surgical risk is physiologic reserve, frailty, and specific medical conditions such as cardiac, pulmonary, and kidney disease. Each is assessed before surgery is scheduled. That evaluation, rather than a birth year, determines whether an older patient is a candidate for repair.

The Iskandar Complex Hernia Center is led by Dr. Mazen E. Iskandar, MD, FACS, a board-certified surgeon who has held the Surgeon of Excellence in Hernia Surgery designation since January 2024. The center is one of only two Hernia Centers of Excellence in North Texas, accredited by the Surgical Review Corporation in October 2025.

hernia surgery safe for elderly

Is there an age limit for hernia surgery?

There is no fixed upper age limit for hernia repair. As of 2026, repairs are performed in patients in their eighties and nineties. What governs the decision instead is whether the hernia is symptomatic and whether the patient has the physiologic reserve to tolerate an operation and recover from it. Surgeons assess both. Candidacy is confirmed through that evaluation rather than an age cutoff.

What are the risks of leaving a hernia untreated in an older adult?

An untreated hernia can become incarcerated, meaning trapped and no longer reducible, and can progress to strangulation, in which blood supply to that tissue is cut off and emergency surgery is required. Emergency repair carries higher morbidity and mortality than planned elective repair, and the gap is widest in older patients. Femoral hernias carry a disproportionately high strangulation risk. Symptomatic hernias are generally repaired electively, though hernias causing no symptoms are sometimes monitored.

At The Iskandar Complex Hernia Center, patients with symptomatic hernias are evaluated so the decision can be made deliberately rather than in an emergency department. Dr. Iskandar’s practice is limited to complex hernia repair, which allows evaluation to focus on the timing and technique a specific hernia calls for.

What health conditions are assessed when deciding whether an older patient can have hernia surgery?

Preoperative assessment in an older patient covers cardiac function, pulmonary function and chronic lung disease, diabetes and glycemic control, kidney and liver function, nutritional status, cognitive status, mobility and functional independence, and current medications including blood thinners. The purpose is twofold. It establishes whether the patient can tolerate anesthesia and the recovery period, and it identifies conditions that can be improved before surgery.

How is an older patient evaluated before hernia surgery is scheduled?

Evaluation follows a set sequence: consultation and medical history, physical examination, cross-sectional imaging when the hernia is large or complex, structured screening for frailty and functional status, medical clearance and treatment of any conditions found, then scheduling. That step is not a practice-specific addition. As of 2026, the American College of Surgeons geriatric surgery standards define preoperative screening for frailty, nutrition, cognition, and mobility as a recognized standard for older elective surgical patients.

Dr. Iskandar evaluates each patient personally rather than delegating the workup, and his consultations are structured around listening before recommending. Patients who arrive expecting to be told they are too old for surgery instead get a full account of what was assessed and why.

Experience renowned expertise and unparalleled compassion from the leader in hernia repair.

Is anesthesia safe for an elderly patient having hernia surgery?

Anesthesia is administered safely to older adults undergoing hernia repair, with the anesthetic plan matched to the patient’s cardiac, pulmonary, and cognitive status. That plan is selected during the preoperative assessment, and considerations specific to older patients, including postoperative confusion and the return of baseline thinking and memory, are factored into the selection. An anesthesiology assessment is part of the workup.

Does recovery take longer after hernia surgery at an older age?

Recovery of baseline strength and independence often takes longer in older patients. Surgical planning accounts for that. Discharge planning, home support, and early mobility are arranged before surgery, and the measure that matters is the return to independent function rather than the wound healing timeline.

The Iskandar Complex Hernia Center is a solo practice, and Dr. Iskandar follows his own patients through recovery. The surgeon who assessed a patient’s reserve before surgery is the same one reviewing his progress afterward.

Is a robotic-assisted or minimally invasive approach safer for an older patient?

Minimally invasive and robotic-assisted repairs use smaller incisions and less abdominal wall disruption than open repair, which is relevant for patients with limited physiologic reserve. They are not universally applicable. Large or complex defects, including those requiring component separation or abdominal wall reconstruction, are repaired open. Technique is selected from the hernia’s characteristics and the patient’s condition rather than applied as a default.

The Iskandar Center performs robotic-assisted, laparoscopic, and open repairs, including abdominal wall reconstruction and non-mesh options such as the Shouldice repair. Dr. Iskandar’s exclusive focus on complex hernia surgery means the approach is chosen for the hernia rather than limited to a single technique.

Can a patient who was told they are too high-risk for hernia surgery still be a candidate?

Being declined for hernia repair is not always a permanent determination. Some limiting factors are modifiable, including nutritional status, obesity, glycemic control, smoking, deconditioning, and medication management, and can be addressed over a period of weeks to months. Other declines reflect the technical demands of the repair relative to a given practice’s focus rather than the patient’s fitness for surgery. Specialist re-evaluation is how the two are distinguished.

Dr. Iskandar, a Surgeon of Excellence in Hernia Surgery, limits his practice to complex hernia repair, and patients are frequently referred to The Iskandar Complex Hernia Center after being told elsewhere that nothing further can be done. For particularly large hernias, he uses botulinum toxin preparation before repair to relax the abdominal wall muscles.

What should a family member ask at a consultation about an older parent’s hernia surgery?

Six questions cover the candidacy decision: what is being assessed to determine whether the patient can tolerate surgery; whether the hernia is symptomatic enough to warrant repair now; what would happen if repair were delayed; which of the patient’s conditions could be improved before surgery; what recovery of independence is expected to look like; and what symptoms would signal an emergency. Each is answerable at a first consultation.

Consultations at The Iskandar Complex Hernia Center in Waxahachie are structured to answer exactly these questions, and family members are welcome in the room. Dr. Iskandar sees patients from across Dallas–Fort Worth, and his approach is to listen before recommending anything.

Key Takeaways: Hernia Surgery in Older Adults

  • Age alone is not a contraindication to elective hernia repair; surgical risk in older adults reflects physiologic reserve, frailty, and specific medical conditions.
  • No fixed upper age limit applies to hernia repair; the decision turns on whether the hernia is symptomatic and whether the patient can tolerate surgery.
  • Emergency repair after a hernia becomes incarcerated or strangulated carries higher morbidity and mortality than planned elective repair, particularly in older patients.
  • Structured preoperative screening for frailty, nutrition, cognition, and mobility is a recognized standard in the evaluation of older elective surgical patients.
  • Being declined for surgery is not always permanent; nutritional status, glycemic control, smoking, and deconditioning can often be improved before re-evaluation.

If you are weighing hernia surgery for an older parent, a consultation at The Iskandar Complex Hernia Center in Dallas–Fort Worth is an evaluation of candidacy, not a commitment to an operation. Schedule a consultation.


source https://iskandarcenter.com/hernia-surgery/is-hernia-surgery-safe-for-elderly-patients/

Monday, August 31, 2026

Is It Worth Traveling to a Hernia Specialist?

Traveling for surgery adds cost, time away from home, and coordination that local care does not require. Whether that tradeoff is justified depends less on distance than on the hernia itself.

Is It Worth Traveling to a Hernia Specialist?

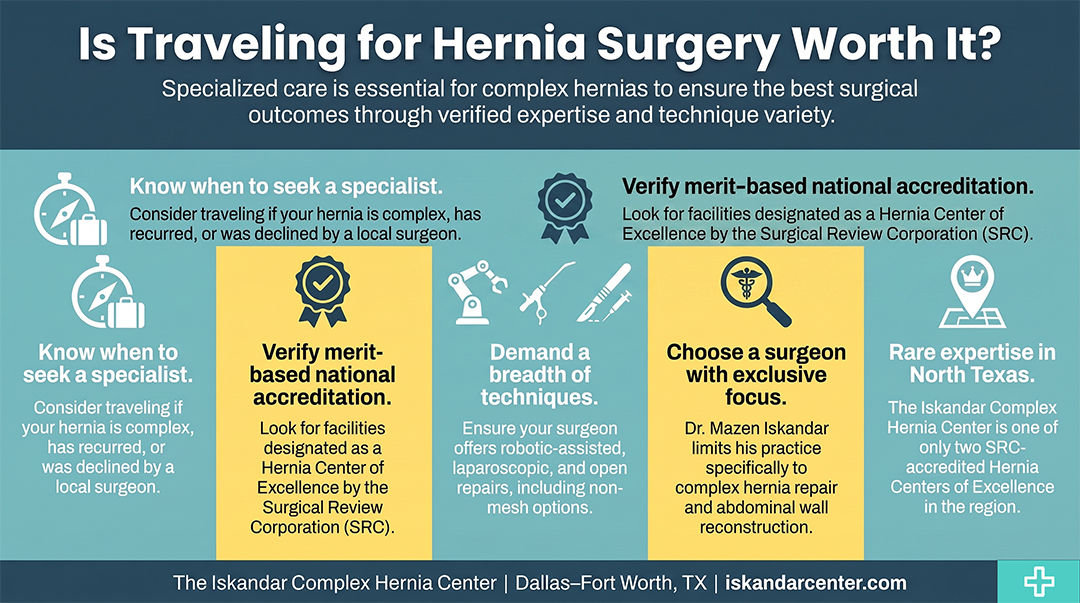
Traveling to a hernia specialist is generally warranted when a hernia is complex, has recurred after a prior repair, or has been declined by a local surgeon. Those repairs demand volume and technique breadth. Before booking travel, patients can verify exclusive focus on hernia repair, merit-based national accreditation, and access to robotic-assisted, laparoscopic, and open approaches including non-mesh options.

The Iskandar Complex Hernia Center is one of only two Hernia Centers of Excellence in North Texas designated by the Surgical Review Corporation (SRC). Its founder, Dr. Mazen E. Iskandar, MD, FACS, earned SRC’s Surgeon of Excellence in Hernia Surgery accreditation and limits his practice to complex hernia repair and abdominal wall reconstruction.

Traveling to a Hernia Specialist

What distinguishes a dedicated hernia specialist from a general surgeon who repairs hernias?

A dedicated hernia specialist limits their practice to hernia repair and abdominal wall reconstruction, while a general surgeon treats hernias alongside gallbladder, bowel, and other abdominal procedures. The distinction is verifiable, not self-declared. As of 2026, the Surgical Review Corporation’s Surgeon of Excellence in Hernia Surgery and Hernia Center of Excellence programs are national, merit-based accreditations requiring volume benchmarks, outcomes data, safety protocols, facility assessments, and chart audits.

Dr. Iskandar earned SRC’s Surgeon of Excellence in Hernia Surgery accreditation in January 2024. The Iskandar Complex Hernia Center followed in October 2025 with its Hernia Center of Excellence designation, one of only two in North Texas. He is board certified by the American Board of Surgery and a Fellow of the American College of Surgeons.

What makes a hernia case complex enough to justify traveling for treatment?

A hernia case justifies travel when it has recurred after one or more prior repairs, involves prior mesh complications, or presents with loss of domain. Large ventral, incisional, hiatal, and paraesophageal hernias fall into the same category, as do repairs requiring component separation or transversus abdominis release. No single technique covers this range. These repairs draw on a range of reconstruction techniques rather than one default approach.

The Iskandar Complex Hernia Center focuses exclusively on complex hernia treatment and repair. Dr. Iskandar performs robotic-assisted, laparoscopic, and open procedures, including component separation, transversus abdominis release, and non-mesh options such as the Shouldice repair.

How many trips does an out-of-area patient need to make for a hernia repair?

An out-of-area hernia repair follows three stages: evaluation, surgery, and post-operative follow-up, with imaging and operative records from prior repairs often reviewed before the patient travels. Trip count depends on the repair planned. Post-operative follow-up is scheduled after surgery rather than fixed in advance. Typically, all records including imaging studies and scans are sent for screening and evaluation. An office visit is then scheduled for a full evaluation and when appropriate surgery can be performed that same week. The type of surgery dictates the recovery and the need to stay around for a short stay. A post op visit is arranged prior to traveling back home.

The Iskandar Complex Hernia Center, a designated Hernia Center of Excellence, sits a 35-minute drive from Dallas-Fort Worth International Airport, where rental cars, taxis, and rideshare are readily available. Surgery is performed at Baylor Scott & White Medical Center – Waxahachie, a full-service hospital with free valet parking at the entrance.

Can the initial consultation be handled remotely for a patient traveling from outside the region?

Pre-travel evaluation for destination hernia care generally begins with review of imaging, operative reports from prior repairs, and medical history, much of which can be transmitted in advance. Records often arrive before the patient does. That review shapes what the first in-person appointment covers. A video visit can be arranged if the patient is a Texas resident.

The Iskandar Complex Hernia Center accepts physician referrals and welcomes imaging and operative reports from prior repairs. Dr. Iskandar’s approach with patients who have been living with pain for years is listen-first and non-judgmental, and the first appointment is not rushed.

How long does an out-of-area patient need to stay near DFW after hernia surgery before traveling home?

Length of stay in the Dallas-Fort Worth area after hernia surgery depends on the repair performed, whether the approach was minimally invasive or open, and the surgeon’s post-operative assessment. Follow-up determines clearance to travel. That assessment is made after surgery rather than scheduled in advance. The follow up is dictated by the complexity of the procedure. For most minimally invasive operations, follow up can be arranged a few days after surgery.

Hotels are available in Waxahachie, with Dallas and Fort Worth options relatively close to The Iskandar Complex Hernia Center. Some out-of-state patients choose to stay nearby until their first follow-up appointment before heading home.

Can a patient’s local surgeon manage follow-up care after traveling for the repair?

Shared follow-up is common in destination surgical care, with the operating surgeon directing the post-operative plan and a local physician handling routine wound checks and interval care. Operative notes and imaging follow the patient. Both physicians work from the same record, with the operating surgeon retaining responsibility for decisions about the repair itself.That being said, continuity of care is preferred for several reasons and every effort is made for the operating surgeon to continue taking care of the patient.

The Iskandar Complex Hernia Center, a practice limited to hernia surgery and abdominal wall reconstruction, receives referrals from surgeons and physicians in North Texas and beyond, including from outside the state. Dr. Iskandar also serves as Associate Professor of Surgery at Texas A&M School of Medicine.

How does insurance work when a patient travels out of network or out of state for hernia surgery?

As of 2026, coverage for out-of-state hernia surgery depends on the plan’s out-of-network benefits, and patients typically verify benefits and obtain prior authorization before traveling. Network status can differ between the facility and the surgeon. Each is verified separately. Some plans consider single-case agreements when a needed procedure is not available in network.

Experience renowned expertise and unparalleled compassion from the leader in hernia repair.

Is traveling to a specialist worth it after a hernia repair has already failed locally?

A hernia that has recurred after a prior repair is among the clearest indications for specialist evaluation, because reoperative surgery works through scarred tissue planes and previously placed prosthetic mesh. Altered anatomy narrows the technical options available. These repairs may require abdominal wall reconstruction techniques that are not performed at every center.

Dr. Iskandar limits his practice to complex hernia repair and abdominal wall reconstruction, and receives referrals from surgeons whose patients have already had one or more repairs. The Iskandar Complex Hernia Center’s concentrated experience in reoperative repair reflects that referral pattern.

Key Takeaways: Traveling to a Hernia Specialist

  • Traveling to a hernia specialist is most often warranted when a hernia is complex, has recurred after a prior repair, or was declined locally.
  • A dedicated hernia specialist limits practice to hernia repair and abdominal wall reconstruction, unlike a general surgeon treating hernias alongside other abdominal procedures.
  • Surgical Review Corporation accreditations, Surgeon of Excellence in Hernia Surgery and Hernia Center of Excellence, require documented volume, outcomes data, and chart audits.
  • The Iskandar Complex Hernia Center is one of only two Hernia Centers of Excellence in North Texas, based in Waxahachie near Dallas-Fort Worth International Airport.
  • Coverage for out-of-state surgical care depends on a plan’s out-of-network benefits, and network status can differ between the facility and the surgeon.

Schedule a consultation with Dr. Iskandar at The Iskandar Complex Hernia Center, 2360 N Interstate 35 E Rd, Suite 310-B, Waxahachie, TX 75165, or call (469) 800-9832. Imaging and operative reports from prior repairs can be sent ahead of a first visit.

Related Resources

Medically Reviewed By:
Mazen Iskandar, MD, FACS
Board-Certified General Surgeon
Fellowship-Trained Minimally Invasive & Bariatric Surgeon
SRC-Accredited Surgeon of Excellence in Hernia Surgery
Last reviewed August 31, 2026


source https://iskandarcenter.com/hernia-surgeon/is-it-worth-traveling-to-a-hernia-specialist/

Friday, June 26, 2026

Robotic Subcutaneous Onlay Repair

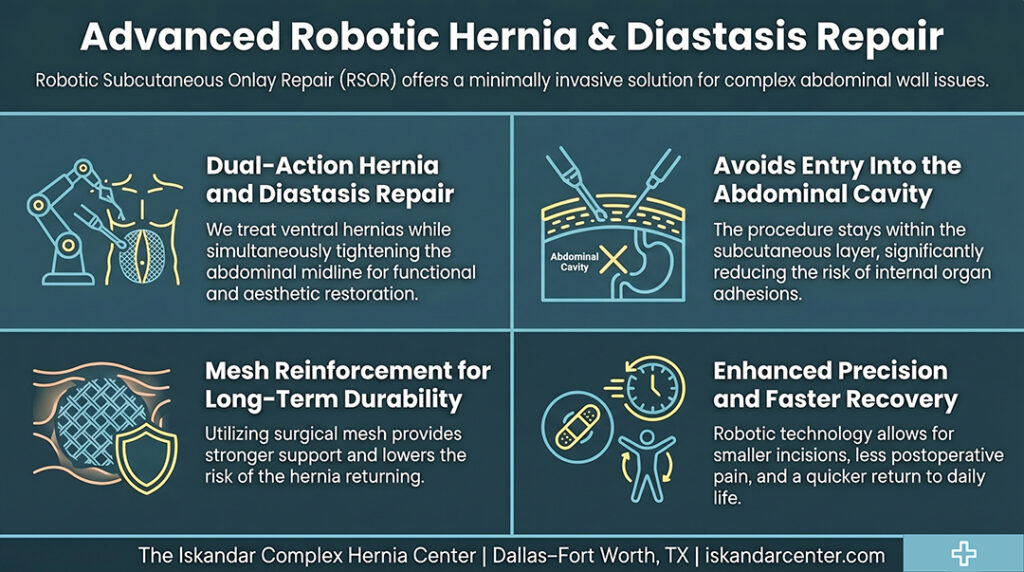
Robotic Subcutaneous Onlay Repair is an advanced minimally invasive procedure used to treat ventral, incisional, and umbilical hernia defects of the abdominal wall that are associated with diastasis recti. This technique utilizes robotics and endoscopy to access the subcutaneous tissue layer beneath the skin and above the muscle, allowing the surgeon to repair the hernia without entering the abdominal cavity. By avoiding deeper planes of the abdomen, this approach reduces certain risks while still reinforcing the abdominal wall with surgical mesh for long-term durability. Surgery in this space also allows for complete plication or tightening of the diastasis similar to what is done in an abdominoplasty or “tummy tuck”. However, no excess skin is removed.

This methodology is gaining attention in the United States as technology continues to evolve and surgeons seek techniques that balance effectiveness, safety, and recovery for the patient.

Technique Overview and Surgical Methodology

During a robotic subcutaneous onlay repair, small incisions in the lower abdomen are made in the skin to allow insertion of robotic instruments. Through careful dissection, a working space is created within the subcutaneous tissue above the fascia of the abdominal wall. This space allows the surgeon to visualize the hernia defect using endoscopy while maintaining precise control through robotics.

Once the hernia sac is reduced, the defect in the muscle is typically closed using surgical suture. Diastasis recti is also addressed to restore proper midline tension and support by plicating or tightening the rectus abdominis muscle along the entire abdomen.

After closure, a surgical mesh is placed over the repaired defect in an onlay position, reinforcing the tissue and distributing tension across the abdominal wall. The mesh is secured using a combination of fixation techniques, which may include additional suture placement depending on the surgeon’s preference and the specific anatomy of the patient.

Anatomical terms of location are critical in this approach, as the procedure takes place entirely within the subcutaneous plane, avoiding entry into deeper layers such as the peritoneal cavity. This distinction separates it from techniques like laparoscopy-based intraperitoneal repairs.

Robotic Subcutaneous Onlay Repair

Mesh vs. No Mesh in Robotic Subcutaneous Onlay Repair

In most adult ventral, incisional, and umbilical hernia repairs, surgical mesh lowers the risk of recurrence compared to closing the defect with surgical suture alone. While direct research comparing robotic mesh repair to robotic no-mesh repair is limited, broader hernia research consistently shows that suture-only repair has a higher chance of failure, especially when the hernia defect is 2 cm or larger. Robotics can improve precision, visualization, and suturing, but it does not change the basic principle that fascia repaired under tension is more likely to reopen over time. A mesh-reinforced repair helps distribute tension across the abdominal wall and provides stronger long-term support. No-mesh repair may be considered only in select cases, such as very small primary umbilical hernias in low-risk patients, but the tradeoff is usually a higher recurrence risk.

Indications and Patient Selection

Robotic subcutaneous onlay repair is most commonly indicated for small to moderate ventral hernia defects, including umbilical hernia and select incisional hernia cases. It may also be considered in patients with diastasis recti, where reinforcement of the abdominal wall provides both functional and aesthetic benefits.

This minimally invasive procedure is often appropriate for patients who may benefit from avoiding intraperitoneal surgery, such as those with prior abdominal operations or increased risk of adhesions. Careful evaluation, including imaging and physical examination, helps determine whether this approach is the best option.

Outcomes and Clinical Results

Early research and clinical experience suggest favorable outcomes with robotic subcutaneous onlay repair. Patients often experience reduced postoperative pain, shorter recovery times, and improved cosmetic results due to smaller incisions and minimal disruption of deeper tissue layers.

The use of robotics enhances precision during dissection and suturing, which may improve the overall result and consistency of the repair. While long-term data is still developing, short- to mid-term findings indicate low recurrence rates when surgical mesh is used appropriately.

As with any evolving surgical technique, ongoing research is essential to better understand long-term durability, complication rates, and patient satisfaction compared to other established approaches.

Risks and Potential Complications

Although this technique avoids entering the abdominal cavity, it is not without risk. The most common complication associated with subcutaneous approaches is seroma formation, where fluid collects in the space created during dissection. The risk of seroma formation is lowered by using a drain that is typically removed on the first post-operative visit.

Other potential risks include infection, wound healing issues involving the skin, and discomfort related to mesh placement. In rare cases, patients may experience chronic pain or issues related to the surgical mesh or fixation methods.

Because the repair is performed within the subcutaneous tissue, careful technique is required to minimize damage to surrounding structures and ensure proper healing of the abdominal wall.

Comparison to Other Hernia Repair Techniques

Compared to traditional open onlay repair, the robotic approach reduces trauma to the patient and improves visualization during surgery. Unlike laparoscopy or intraperitoneal techniques, robotic subcutaneous onlay repair avoids placing mesh inside the abdomen, which reduces the risk of adhesion to internal organs.

However, other approaches such as retromuscular or preperitoneal repairs may offer advantages in certain cases, particularly for larger or more complex hernia defects. These techniques position the mesh deeper within the abdominal wall, which may reduce some types of complication.

The choice of technique ultimately depends on the size and location of the hernia, the patient’s anatomy, and the surgeon’s expertise.

Special Considerations

Understanding the anatomy of the abdominal wall, including the relationship between muscle layers, fascia, and subcutaneous tissue, is essential for successful outcomes. Conditions such as prior surgery, altered anatomy, or birth defect-related changes may influence the surgical plan.

In addition, patient-specific factors such as overall health, activity level, and risk factors for recurrence must be considered when selecting the appropriate repair technique.

Evidence and Ongoing Research

Current research on robotic subcutaneous onlay repair is still emerging, with most available data derived from smaller series and early clinical studies. These studies suggest that the technique is safe and effective for appropriately selected patients, particularly those with smaller midline defects.

As more surgeons adopt robotics and refine their methodology, larger studies and comparative trials are expected to provide deeper insight into outcomes, complication rates, and long-term durability.

Dr. Iskandar’s Thoughts on the Technique

Robotic subcutaneous onlay repair is a great option to address small hernias that are associated with diastasis recti. he incisions are typically hidden in the waist line. The ideal candidate for this operation would be someone who is not overweight and without excess skin. If excess skin is present, an abdominoplasty performed by a plastic surgeon would be a better option.

Conclusion

Robotic Subcutaneous Onlay Repair is an innovative minimally invasive procedure that expands the options available for hernia treatment. By combining robotics, endoscopy, and careful anatomical planning, this technique allows surgeons to repair hernia defects while minimizing disruption to the abdomen.

Although further research is needed to fully define its long-term role, early results are promising. For the right patient, this approach can provide an effective balance of safety, recovery, and durable repair of the abdominal wall.


Medically Reviewed By:
Mazen Iskandar, MD, FACS
Board-Certified General Surgeon
Fellowship-Trained Minimally Invasive & Bariatric Surgeon
SRC-Accredited Surgeon of Excellence in Hernia Surgery
Last reviewed June 26, 2026


source https://iskandarcenter.com/hernia-surgery/robotic-subcutaneous-onlay-repair/

Tuesday, May 5, 2026

How long does hernia surgery take?

If you or a loved one has been diagnosed with a hernia, one of the first questions you’re likely to ask is: how long does hernia surgery take? It’s a completely reasonable concern — understanding what to expect before, during, and after your procedure helps reduce anxiety and allows you to plan your recovery properly.

The short answer is that most hernia surgeries take between 1- 3 hours, depending on a number of factors. But the full picture is more nuanced and highly depends on the type, size of the hernia, and previous surgical history to name a few. As a rule, performing safe and successful surgery is the goal independent of time. At the Iskandar Complex Hernia Center, Dr. Iskandar and his team believe that an informed patient is better prepared for a successful outcome. This guide walks you through everything you need to know about hernia surgery duration.

Quick Reference: Hernia Surgery Times at a Glance

What Is a Hernia and Why Does It Require Surgery?

A hernia occurs when an internal organ or fatty tissue pushes through a weak spot in the surrounding muscle or connective tissue of the abdominal wall. The most common locations include the groin, navel, and upper abdomen. Left untreated, hernias rarely resolve on their own — and some can progress to a serious complication called strangulation, where blood supply to the organ is cut off.

Hernia repair is the only definitive treatment. During the procedure, a surgeon returns the protruding tissue to its correct position and reinforces the weakened wall using either a surgical suture, surgical mesh, or a combination of both.

Factors That Affect How Long Hernia Surgery Takes

No two hernia surgeries are identical. The duration of your procedure will depend on several key factors that Dr. Iskandar will evaluate during your consultation:

1. Type and Size of the Hernia A small, uncomplicated umbilical hernia takes far less time to repair than a large incisional hernia involving significant scar tissue from a previous surgical incision. The bigger and more complex the defect in the abdominal wall, the longer the repair.

2. Surgical Approach: Open vs. Laparoscopy vs. Robotic Surgery The method used significantly impacts how long you’ll be in the operating room. Laparoscopy and robotic surgery are minimally invasive procedures that typically involve smaller incisions and more precise instrument work, which can add some setup time but generally results in faster healing and fewer wound complications. Open surgery may be faster in straightforward cases, but is sometimes necessary for complex or recurrent hernias.

3. Anesthesia and Patient Health Patients with significant underlying health conditions may require more preparation time before anesthesia is administered. A thorough pre-operative health evaluation ensures that medication dosages are appropriate and that the patient is optimally prepared for surgery.

4. First-Time vs. Recurrent Hernia A recurrent hernia — one that has returned after a prior repair — is almost always more technically challenging. Scar tissue from the previous procedure can obscure the surgical field, increasing operating time and the risk of inadvertent injury to surrounding structures.

5. Emergency vs. Elective Surgery Emergency hernia surgery performed for incarceration or strangulation — where the hernia is trapped and bleeding or tissue death is a risk — takes longer than a planned, elective procedure.

Experience renowned expertise and unparalleled compassion from the leader in hernia repair.

How Long Does Each Type of Hernia Surgery Take?

Inguinal Hernia Surgery

Inguinal hernia surgery is the most commonly performed hernia repair in the world. An inguinal hernia occurs when tissue — usually part of the intestine — protrudes through a weak spot in the muscles of the groin. Inguinal hernia surgery typically takes 60 to 90 minutes, depending on whether the open or laparoscopic approach is used and whether the hernia is on one or both sides (bilateral repair takes longer).

Signs and symptoms that indicate it’s time for repair include a visible bulge in the groin, discomfort during exercise or lifting, and a persistent aching sensation.

Umbilical Hernia Surgery

Umbilical hernias occur at the navel and are among the most straightforward repairs. Most cases are completed in 60-90 minutes as an outpatient procedure under general anesthesia. Recovery is typically smooth, with most patients returning to light activity within one to two weeks.

Hiatal Hernia Surgery

Hiatal hernias are fundamentally different from other hernia types — they involve the gastrointestinal tract pushing upward through the diaphragm into the chest cavity. Because the anatomy is more complex and the procedure requires careful manipulation near critical structures, hiatal hernia surgery typically takes 2 to 3 hours. These procedures are most commonly performed laparoscopically.

Ventral and Incisional Hernia Surgery

Ventral hernias develop through the anterior abdominal wall, while incisional hernias occur at the site of a previous surgical incision. These repairs often involve larger mesh placement and, in complex cases, muscle reconstruction. Expect a duration of 1 to 2.5 hours for straightforward cases, and longer for complex abdominal reconstruction.

Complex Hernia Surgery

At the Iskandar Complex Hernia Center, Dr. Iskandar specializes in complex abdominal wall reconstruction — cases involving large defects, recurrent hernias, and patients with prior mesh complications. These procedures can take 5-6 hours or more and require advanced surgical expertise to achieve a durable result while minimizing the risk of infection, fluid accumulation (seroma), and other complications.

Laparoscopic vs. Open vs. Robotic Surgery: A Duration Comparison

Robotic surgery, offered at the Iskandar Complex Hernia Center, uses a highly advanced robotic platform that gives Dr. Iskandar three-dimensional visualization and wristed instrument control. While robotic surgery can add some time to the procedure, it offers significant advantages in complex cases — particularly in reducing the risk of post-operative pain, bleeding, and wound complications compared to traditional open repair.

Your Total Time at the Facility: More Than Just Surgery

When patients ask “how long does hernia surgery take,” they often mean the entire day — not just the time in the operating room. Here’s a realistic breakdown of your total time at the surgery center or hospital:

  • Pre-operative preparation: 1-2 hours (check-in, IV placement, anesthesia assessment, surgical site marking)
  • The surgery itself: 1– 3+ hours (depending on hernia type and approach)
  • Post-anesthesia recovery (PACU): 1–2 hours (monitoring as anesthesia wears off, analgesic administration for pain management)
  • Discharge preparation: 30–60 minutes

Most patients undergoing elective, minimally invasive hernia repair can expect to spend around 5-6 hours total at the facility before heading home the same day.

Is Hernia Surgery Outpatient or Inpatient?

The vast majority of hernia repairs performed at the Iskandar Complex Hernia Center are same-day, outpatient procedures. Patients go home the same evening and recover in the comfort of their own home. A hospital stay is generally required only for:

  • Hiatal hernia repairs requiring extended monitoring
  • Emergency surgery for incarcerated or strangulated hernias
  • Complex abdominal wall reconstruction cases
  • Patients with significant comorbidities requiring post-operative medical management

Frequently Asked Questions

How long does inguinal hernia surgery take?

Inguinal hernia surgery typically takes between 30 and 90 minutes. Bilateral (both sides) repair takes longer, as does laparoscopic repair compared to a simple open approach in some cases.

How long will I be at the hospital for hernia surgery?

Most patients spend 4 to 6 hours at the surgical facility from check-in to discharge, even if the surgery itself takes under an hour.

Can hernia surgery be done in under an hour?

Sometimes small umbilical hernias can be repaired in that time frame especially if no mesh is used. However, surgical time always depends on what the surgeon encounters once the procedure begins.

How long does recovery take after hernia surgery?

Most patients return to light activity within 1–2 weeks and resume full exercise and physical labor within 4–6 weeks. Complete internal healing takes 3–6 months.

What is the most common complication after hernia surgery?

The most frequently reported post-operative issues include seroma (fluid collection beneath the wound), infection, and temporary pain at the repair site. At the Iskandar Complex Hernia Center, these risks are minimized through meticulous surgical technique and thorough post-operative care.

Is robotic hernia surgery better than laparoscopic?

For complex and recurrent hernias, robotic surgery offers advantages in precision and visualization. Dr. Iskandar will recommend the best approach based on your individual anatomy, hernia characteristics, and health history.

Schedule a Consultation at the Iskandar Complex Hernia Center

Whether you’ve just been diagnosed or have been living with a hernia for years, the right time to seek expert care is now. Delaying hernia repair increases the risk of complications — including incarceration, strangulation, and emergency surgery.

Dr. Iskandar is a board-certified hernia specialist with extensive experience in open, laparoscopic, and robotic hernia repair. The Iskandar Complex Hernia Center is dedicated exclusively to the diagnosis and surgical treatment of all hernia types — from routine inguinal repairs to the most complex abdominal wall reconstructions.

Call us today to request a consultation and find out which procedure is right for you. You deserve a surgeon who will take the time to understand your case and deliver results built to last.


source https://iskandarcenter.com/hernia-surgery/how-long-does-hernia-surgery-take-2/

Monday, April 27, 2026

Can You Keep Working With a Hernia or Should You Stop? What Injured Workers Need to Know About Light Duty, Surgery, and Returning to Work

If you developed a hernia on the job, you’re likely facing a question that no one is giving you a straight answer to: can you keep working, or do you need to stop? At the Iskandar Complex Hernia Center, we understand that the decision isn’t purely medical — it’s financial, legal, and deeply personal. This guide walks you through what you need to know right now, from recognizing serious signs and symptoms to understanding your rights as an injured worker.

Can You Actually Keep Working With a Hernia?

The honest answer is: it depends. A hernia occurs when tissue or an organ pushes through a weak point in the surrounding muscle or abdominal wall. The most common types in workplace injuries are inguinal hernias, which develop in the groin area, and umbilical hernias, which form near the navel. How much pain you’re in and how physically demanding your job is will largely determine whether continuing to work is reasonable.

For workers in sedentary roles, light activity may be tolerable in the short term. But for those who lift, carry, strain, or spend long hours on their feet, working through a hernia without medical guidance significantly raises your risk of making it worse. Factors like obesity, repeated coughing, or anything that puts pressure on the abdomen can accelerate deterioration and create complications that require more involved intervention.

One important point most workers don’t consider: delaying a doctor’s visit or continuing to work without reporting the injury can actually undermine a workers’ compensation claim later. Report the injury, see a health professional, and get everything documented.

guidelines on working with a hernia

How to Know When a Hernia Is Too Serious to Push Through

Some hernias can be monitored with a watchful approach. Others require immediate attention. Knowing the difference could protect your health.

Seek emergency care immediately if you experience any of the following:

  • A bulge in the abdomen or groin that becomes hard and cannot be pushed back in
  • Sudden, severe pain at the hernia site
  • Nausea, vomiting, or signs of bowel obstruction
  • Skin at the hernia site that appears red, purple, or discolored
  • Difficulty breathing or significant abdominal pressure with no relief

These are signs of a strangulated hernia — a condition in which the herniated tissue loses its blood supply. This is a surgical emergency that can cause permanent damage to the gastrointestinal tract if not treated immediately. Ignoring these symptoms in an effort to finish a shift is not worth the risk.

What Is Light Duty and Can You Request It After a Hernia?

Light duty refers to modified work assignments that stay within the physical restrictions set by your treating physician. In practice, this might mean no heavy lifting, limited time on your feet, or a shift to desk-based tasks. For workers with a hernia diagnosis, light duty can create the space needed to continue earning income while avoiding further strain on the injured muscle and surrounding tissue.

If your employer is covered by workers’ compensation, they are generally required to accommodate a physician’s written restrictions. A doctor’s note outlining specific limitations — no lifting over a certain weight, no exercise that strains the abdomen, no repeated bending — is your most effective tool. Get those restrictions in writing and keep a copy.

There is often a fear of being labeled a problem employee for requesting accommodations. That concern is valid, but the legal protections discussed below exist precisely to address it. Your health and your claim both depend on following medical guidance, not pushing through against your doctor’s orders.

During light duty, if your modified position pays less than your normal wage, partial disability benefits through workers’ comp may make up a portion of the difference. Ask your claims representative about your specific benefits.

When Surgery Is Necessary — And What That Means for Your Job

A surgeon will typically recommend hernia repair surgery when the hernia is growing, causing significant pain, or carries a meaningful risk of strangulation. Watchful waiting is sometimes appropriate for smaller, asymptomatic hernias — but that decision should be made with a qualified health professional who has reviewed your imaging, your activity level, and your overall health history.

Hernia repair generally involves one of two approaches: open surgery or minimally invasive laparoscopic techniques. Recovery timelines vary depending on the method, the complexity of the hernia, and the patient’s overall health. Many patients return to light activity within one to two weeks, while those in physically demanding roles may need four to twelve weeks before they’re cleared for full duty.

A case that made headlines in early 2025 illustrates why understanding your rights before surgery matters: an Amazon warehouse worker in Las Vegas developed an inguinal and umbilical hernia on the job and was subsequently fired for “non-attendance” while recovering from approved hernia repair surgery — allegedly because an automated system misclassified his approved leave as unexcused absences. aol His case is now in federal court. It’s a clear reminder that documentation and knowing your protections aren’t optional — they’re essential.

Experience renowned expertise and unparalleled compassion from the leader in hernia repair.

Returning to Work After Hernia Surgery: Realistic Timelines and Expectations

Healing from hernia repair takes time, and the pressure to return quickly — from employers, coworkers, or financial stress — is real. But coming back too soon puts your recovery and your abdominal wall at genuine risk. Re-injury means more time out of work and a potentially more complicated path forward.

General return-to-work timelines as a starting point:

  • Desk or light duty: 1–2 weeks post-surgery
  • Moderate physical work: 4–6 weeks
  • Heavy labor or repeated strain: 6–12 weeks, depending on your surgeon’s evaluation

Your surgeon, Dr. Iskandar, will determine when you are cleared for full duty, and that clearance should be based on your individual healing progress — not a predetermined calendar. Workers’ comp typically covers the recovery period, including medical care and a portion of lost wages while you’re unable to work.

Most patients who receive proper care and allow adequate healing time do return to full capacity. The goal at the Iskandar Complex Hernia Center is always a dramatically improved quality of life — and that outcome is most achievable when recovery is taken seriously from the start.

Dealing with a hernia from work and not sure what your next step should be? Start with a consultation with Dr. Iskandar. Contact the Iskandar Complex Hernia Center at (469) 800-9832 or schedule a consultation online.


source https://iskandarcenter.com/abdominal-wall-repair/can-you-keep-working-with-a-hernia-or-should-you-stop-what-injured-workers-need-to-know-about-light-duty-surgery-and-returning-to-work/